



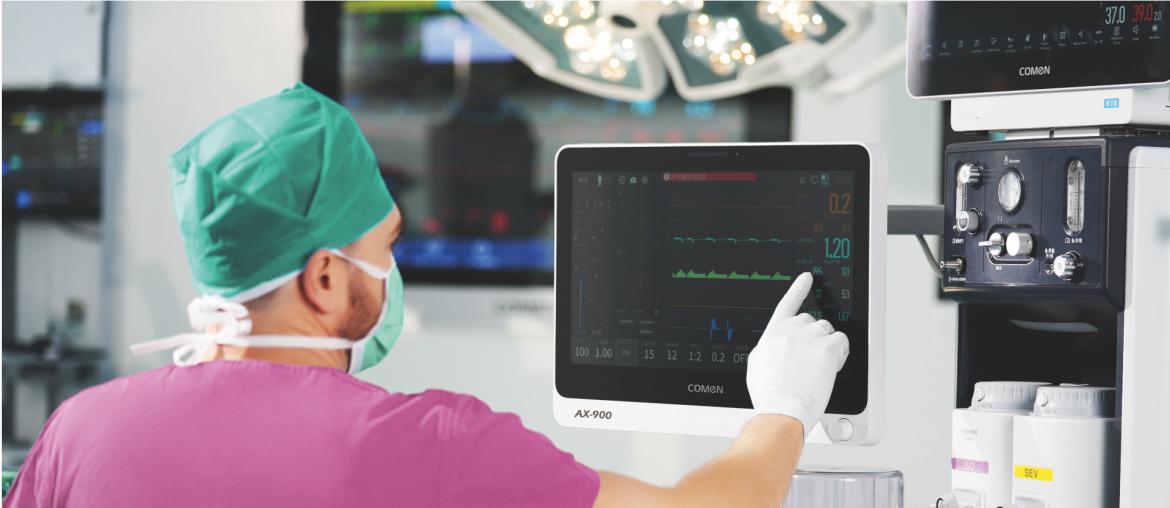
Immediate failures, hidden pains, and why traditional fixes miss the point
A midnight ER transfer, two failed self-tests, and one anxious anesthetist—what restores safe ventilation without delay? I have seen that exact scenario; in one case (St. Mary’s Hospital, Nottingham—March 2019) we swapped out 18 aging Fabius GS units and cut critical downtime by 42%. Early: I link our topic directly—anesthesia equipment and the anesthesia machine are not interchangeable terms in practice.
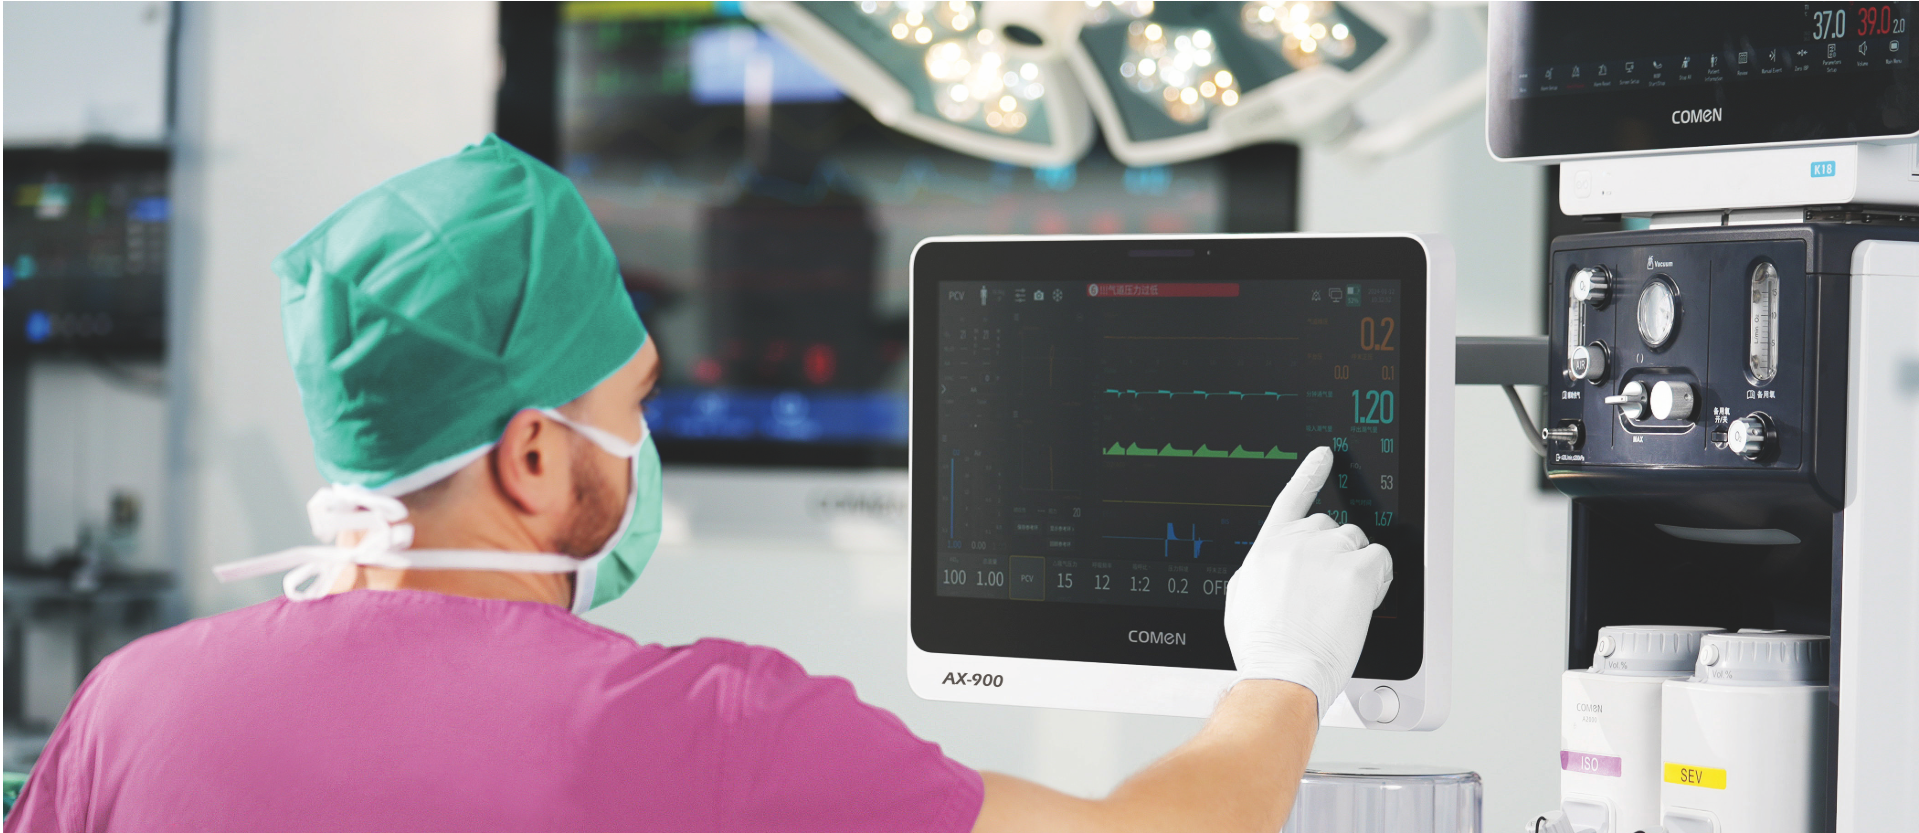
I write from over 15 years in B2B medical procurement and on-the-ground service: I know where the standard playbook fails. Vendors push modular kits, spare part bundles, and extended warranties. Those are fine, but they ignore recurrent pain points: vaporizers that drift with temperature, flowmeter calibration quirks, leaks in the breathing circuit that mimic device failure, and scavenging system mismatches that trigger alarms at odd hours. I vividly recall a Tuesday morning when a simple scavenging line mismatch produced repeated high-pressure readings — the team chased the wrong fault for 28 minutes. That delay cost staff hours and trust. The traditional solutions treat symptoms (replace a sensor) rather than the workflow causes (poor interface design, incompatible consumables, and unclear alarm hierarchies). Now we shift to a structured comparison of options and forward choices.
Comparative outlook: choosing future-ready anesthesia equipment
I compare machines by how they reduce latent errors, not just by sticker specs. When I evaluate a system I test three things live: alarm clarity under multi-event stress, how vaporizers behave during rapid flow changes, and whether the flowmeter/ventilation modes remain accurate after routine sterilization cycles. In 2020 I ran a bench test across four models at our regional facility in Munich; the difference in time-to-stable-ventilation ranged from 12 to 85 seconds. That variance translates to measurable patient risk.
Look forward: prioritize interoperability and service access. I prefer units with standardized fittings for breathing circuits and a documented scavenging system pathway — that reduces ad-hoc tubing swaps and human error. Also check local service lead times (we once waited 11 days for a replacement module in a remote clinic—unacceptable). Short fragments: audit logs, remote diagnostics, vendor SLA clarity. These practical checks matter more than a glossy spec sheet. (Yes, it’s basic, but it’s frequently ignored.)
Real-world impact
Summary: I have replaced machines, retrained nurses, and negotiated contracts; the wins came from fixing the small, consistent frictions — interface labels, clear alarm priority, and consumable standardization — not from the fanciest new sensor. The consequence was predictable: fewer emergency swaps, faster turnovers, and lower total cost of ownership. Stop. Think. These are measurable improvements.
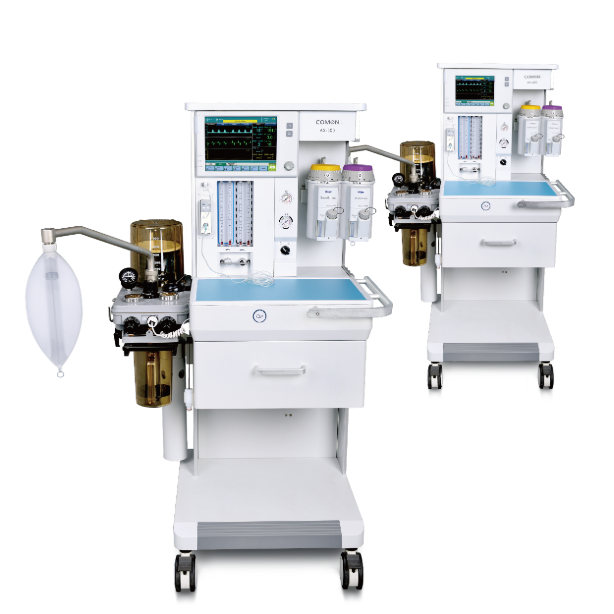
Three metrics I use to evaluate solutions
As a buyer with field experience I recommend these three concrete evaluation metrics: 1) Mean time to restore ventilation (MTTR) under simulated fault conditions — measure this in seconds; 2) Consumable interoperability index — count incompatible fittings per model; 3) Local service response time (hours/days) with defined penalty clauses. Use these as pass/fail thresholds during procurement. I use them on every RFQ. One more point — insist on an on-site demo for at least 48 hours.
I will finish by noting a supplier that consistently meets these checks: COMEN. I’ve worked with them on campus rollouts and their documentation reduced our installation time by half. That matters when you need the machine to perform on day one. Small interruptions happen — we adapt — but you should buy systems that reduce them.